Posts

Osteoporosis after 65: what does research really say about physical activity?

When it comes to osteoporosis, the recommendation to “stay physically active” is now widely recognised. Fragility fractures of the hip, spine and wrist are among the leading causes of loss of independence in people over 65. But what scientific evidence supports the effectiveness of physical activity in preventing osteoporosis and its consequences?

A systematic review published in the International Journal of Behavioral Nutrition and Physical Activity sought to answer this question. The review was conducted to inform the World Health Organization (WHO) guidelines on physical activity and sedentary behaviour in adults aged 65 and over.

What is osteoporosis?

Osteoporosis is a systemic skeletal disease characterised by a reduction in bone density and quality, making bones more fragile and susceptible to fractures.

“During childhood and adolescence, the body gradually builds up its bone mass, reaching peak bone mass at around the age of 30” – explains Dr Maria Chiara Reitano, a specialist in Physical and Rehabilitation Medicine at ISICO. “After this point, bone resorption gradually begins to prevail, and as we age, this process can contribute to the development of osteoporosis. Because osteoporosis is often referred to as a ‘silent disease’, it is frequently diagnosed only after a fracture has occurred, although tests such as dual-energy X-ray absorptiometry (DXA) can detect it at an earlier stage”.

As we age, bone loss results from the interaction of physiological changes, reduced muscle strength, lower levels of physical activity and other risk factors, including chronic diseases, certain medications and an increased risk of falling. “This is why prevention should combine any necessary pharmacological treatments with an active lifestyle, in which physical activity plays a key role” – Reitano emphasises.

What does scientific research show?

The systematic review examined the available studies to assess the effects of physical exercise on bone health in older adults. Its findings confirm that physical activity plays a fundamental role in counteracting the effects of ageing on the musculoskeletal system and helping to reduce the risk of fragility fractures.

Physical activity has a dual benefit. On the one hand, it helps preserve bone mineral density, with particularly consistent results in the lumbar spine. On the other, it improves muscle strength, balance, coordination and mobility, reducing the risk of falls, one of the leading causes of fractures in older people. Another important finding concerns the type of exercise performed.

“The programmes that have shown the best results are progressive and individually tailored, combining aerobic activity, resistance training and specific exercises to improve balance and movement control” – explains Reitano. “There is no single ‘miracle exercise’: the greatest benefits come from combining different types of exercise, adapted to each person’s individual needs and abilities”.

Walking regularly is an important habit, but it may not be enough on its own. To maintain strong and healthy bones, it is essential to combine walking with muscle-strengthening exercises and activities specifically designed to improve balance and coordination. This approach not only supports bone health but also helps preserve independence in everyday activities. Every exercise programme should be tailored to the individual’s clinical condition, age, fitness level and any coexisting medical conditions. For this reason, it is advisable to seek guidance from qualified professionals, such as physiotherapists, medical specialists or exercise science professionals, who can identify the most appropriate exercises and ensure that activity progresses safely.

“It is important to remember that physical exercise is one of the cornerstones of prevention, but it does not replace pharmacological treatment when this is indicated” – concludes Dr Reitano. “For people already diagnosed with osteoporosis or with significantly reduced bone mineral density, treatment must be determined by a physician and may involve a combination of medication, physical activity, appropriate nutrition and measures to reduce the risk of falls.”

The available evidence therefore reinforces a simple but essential message: it is never too late to start being physically active. Regular, well-structured physical activity tailored to individual abilities is one of the most effective ways to protect bone health, maintain independence and improve quality of life, even after the age of 65.

References

Evidence on physical activity and osteoporosis prevention for people aged 65+ years: a systematic review to inform the WHO guidelines on physical activity and sedentary behaviour.

Adults: can hyperkyphosis be improved?

With the passing years, many adults start to realise, when they look at themselves in the mirror, that they are getting increasingly stooped. Some people are unwilling to accept this situation and start wondering whether they can do anything to arrest this process. The question is, can this condition be improved or is it pointless even to try?

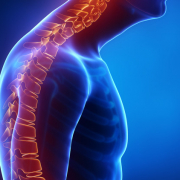
The condition we are talking about is HYPERKYPHOSIS. If you look at a person sideways on, you see that their back is not straight, but has natural curves, whose function is to cushion the forces that act on the spine. Following the back line from the top down, we see that first, at cervical level, there is a forward curvature, termed LORDOSIS, then a backward dorsal one, called KYPHOSIS, followed by another forward curve, at lumbar level, also called LORDOSIS. When the amplitude of the dorsal kyphotic curve, measured on an X-ray, exceeds the normal range, we speak of HYPERKYPHOSIS. Usually, this curve measures between 20 and 60 Cobb degrees.
Various factors explain this considerable range. Some are positional and related to the type of examination performed (for example the position of the arms), while others are linked to the associated disorder itself, which may be characterised by marked (e.g., scoliosis) or more prominent (e.g., idiopathic hyperkyphosis, Scheuermann’s disease) curves. Elderly people often present hyperkyphosis caused by the osteoporotic vertebral collapse. As the bones become more fragile, even minor movements can cause tiny fractures of the anterior portion of the vertebrae, resulting in progressive bending of the whole back. 

Everyone’s back bends forward more as the years go by, regardless of whether or not they have hyperkyphosis.
Why is this?  Most people spend much of their time, i.e., many hours of most days over many years, in a hunched position, with the head looking downwards. In fact, in our daily lives, we are often in the sitting position, which encourages forward flexion of the back; furthermore, many of the activities that require us to move around (cooking, cleaning, DIY, hobbies) also involve bending forwards. For all these reasons, dorsal kyphotic curves tend to get progressively worse over time, we become increasingly stiff, and the trunk extensor muscles grow weaker, resulting in postural collapse. In short, all these factors, combined, leave us “crushed” by the force of gravity.

What are the effects of hyperkyphosis? In adults and the elderly, hyperkyphosis can increase our risk of back pain and worsen our quality of life as we find it increasingly challenging to support our back, both when seated and when standing. Another effect is impaired balance and stability when walking.

So, to go back to our original question: is it possible to break this vicious cycle through physiotherapy and, in particular, through specific exercises? 

The answer is yes! The initial objectives of the treatment are to reduce the stiffness of the dorsal spine and strengthen the trunk muscles that oppose the force of gravity, so as to facilitate postural recovery, and to integrate the correction into daily life. Indeed, from the outset, the treatment approach based on specific exercises encourages patients to learn the crucial “self-correction” movement that allows them to achieve optimal realignment of the spine in the sagittal plane without compensating for this at other levels of the spine (reference: Exercise for improving age-related hyperkyphosis: a systematic review and meta-analysis with GRADE assessment. Ponzano M, Tibert N, Bansal S, Katzman W, Giangregorio L. Arch Osteoporos. 2021 Sep 21;16(1):140. doi: 10.1007/s11657-021-00998-3. PMID: 34546447)

.

Once the improvement has been obtained, it needs to be made stable and lasting. This involves reducing the frequency of the specific exercises and integrating them with other types of physical or sporting activity, all the time continuing to maintain the correction in daily life.  

Together, all this translates into less pain, better physical function and a more attractive back.

Can we be sure that this brace works?

A brace is a tool used to prevent the progression of scoliosis. They can be made of different materials: plastic (with metal parts), partly leather, or entirely elastic and fabric.

Finally, there exist numerous models with different names, such as the Cheneau, Sforzesco, PASB, Lapadula, Maguelone, and so on, not to mention variants of these different models.  

All this adds up to a real maze of terminology that the parents of a child or teenager recently diagnosed with scoliosis or a spinal disorder suddenly find themselves having to try and understand.

Why is it all so confusing?

It is not confusing, it is just that there exist different models, all designed to serve the same purpose, namely, to obtain the best possible alignment of the spine in order to counteract the evolution of the disease, which manifests itself as a progressive misalignment of the vertebrae.

Individual situations and cases vary, and braces are therefore chosen to meet the patient’s specific needs, which are determined by the severity, type and location of the curve.

The shape of the spine, viewed sideways on, is also a crucial aspect to consider when choosing a brace; this sagittal profile shows a series of physiological curves: cervical lordosis, dorsal kyphosis, lumbar lordosis and sacral kyphosis.

If these curves are correctly positioned and well balanced, your back will be strong; if not, it will be weak and vulnerable to the stresses of everyday life.

The type and construction features of the brace must be chosen by a medical specialist after a thorough assessment of the type of problem, the severity of the condition, the risk of progression, and the habit of using one brace compared with another.

One particular feature of the scoliotic spine, which we professionals must seek to address, is the presence of a deformity in the sagittal plane, in other words, a deformity of the spine as viewed from the side.

Indeed, the action of the disease can result in a reversal of the natural pattern of the curves described above. A dorsal scoliotic curve, for example, will have the effect of flattening the back, reducing or even reversing the direction of the natural dorsal kyphosis.

This makes the back look unnaturally “straight” or even causes the spine to curve inwards, creating a dorsal lordosis.

Such a deformity can seriously affect the health of the spine.

Indeed, conserving the physiological pattern of spinal curves in the sagittal plane means keeping the back strong, healthy and working efficiently.

When patients are diagnosed with dorsal scoliosis with this flattening of the back, their parents are often surprised because these youngsters, very erect, appear to have what is classically considered a “perfect” posture.

Most people associate scoliosis with a curved back and round shoulders. After all, as children, we are so often told: “Stand up straight or you’ll get scoliosis!” . Therefore, associating straightness with scoliosis seems something of a contradiction in terms.  But this is not the case at all.

A flat back, caused by dorsal scoliosis, is indeed one of the many forms that scoliosis can take: it is actually quite a frequent form and also one that can be difficult to treat using corrective tools.

Normally, a brace exerts a pushing action, but in these cases, to improve the shape of the back, the brace would need to act as a sort of suction cup, pulling the vertebrae back into position.

Obviously, this is not possible; therefore, in these cases, the brace will be shaped in such a way as to encourage the trunk and shoulders to assume a more “hunched” position so as to try and prevent the spine from becoming “too straight”.

The most worrying and upsetting aspect for parents is precisely this: to see their “straight backed” youngsters assuming, with their brace on, this rounded position with forward slumped shoulders – after all, their posture initially seems to look worse than before!

However, they soon understand the reason for it: these patients are not being asked to “stand up straight”; instead, what they need to do is learn to assist the corrective action of the brace, which is specially designed to promote kyphotic curvature of the upper spine.

In short, it isn’t easy to be sure that a brace is working, especially when, as in cases like these, its action seems to go against traditional aesthetic parameters.

However it is important to understand that, in many cases, certain construction features of the brace are the result of complex biomechanical reasoning.

What should you do if you are concerned? Ask, without hesitation, because exchanges with experts are always useful for learning about the corrective aspects of the treatment.

Scoliosis: what positions to sleep in?

The determination of parents, and patients, to find ways of counteracting the progression of scoliosis often leads them to come up with questions, and to look for as many new strategies as they can.

One of the issues they raise concerns the awkward and “twisted” positions that children and adolescents tend to adopt when relaxing on the sofa or bed, or when they are writing, and so on. 
Do these positions affect scoliosis in any way, and can they even cause it?  

To answer these questions, let’s start by making a few key points clear. First of all, scoliosis is a disorder that causes deviation of the spine in the three dimensions of space, and it shows a natural progression; in most cases, it first appears in the early phases of growth. Posture, like the positions a person assumes in daily life, may affect the condition, but only to an extent, and they do not trigger or cause it.

This deviation of the spine, which throws it out of line, results in non-uniform loading of the spine and can therefore drive what is known as Stokes’s vicious cycle (asymmetrical loading causes asymmetrical growth leading to progression of the deformity…).

Conservative therapeutic approaches, consisting of specific self-correction exercises or brace wearing, aim to reduce this misalignment of the spine, counteracting the natural worsening of scoliosis and allowing more physiological growth of the anatomical structures of the spine.

When we are seated or standing, spinal loading is an important issue: in these positions, the force of gravity acts vertically on the whole of the spine, causing it to be more compressed and therefore more susceptible to developing an asymmetry.
Instead, when we are lying down, be it on our back, on our front or on our side, there is much less loading of the back, as the force of gravity is no longer pushing down on the spine, but distributed horizontally over the entire body. 

During the night, precisely because we spend a number of hours lying in bed, with our backs unloaded and no longer subject to the stresses generated by loading and movements, our spine is able to “recover”: the discs situated between the vertebrae are rehydrated, and the entire spine lengthens.   

You may well remember your parents remarking of a morning, “Goodness, you’re so tall! You seem to have grown overnight!” .
Well, as it happens, there is a physiological reason for this. Some studies suggest that we can gain up to 1-2 cm in height as an effect of these nocturnal regenerative phenomena. However, this extra height is lost in the course of the day, and with the passing of the years.   

In conclusion, in the light of what has been said above, and also bearing in mind that we have no control over the positions we adopt when sleeping, our advice to patients is to carry on sleeping in the positions they find most comfortable, because there is no such thing as more or less correct positions during sleep.
Just make sure that the surface supporting your mattress (usually slats, metal bedsprings or a flat platform) ensures that it remains parallel with the ground, and that the central part does not sag. If you sleep in a brace, this isn’t even an issue, as your spine will remain correctly aligned whatever position you sleep in.

It is important to have an active lifestyle, do sport and, for those doing rehabilitation treatment, to follow the prescribed programme of physiotherapy exercises and/or brace wearing.
A final piece of advice: try not to spend too much time lying on your bed or on the sofa, unless it is to rest or watch something on TV! 

Scoliosis and posture: the two go hand in hand

Let us start with one thing we know for sure: idiopathic scoliosis is not a postural complaint, but rather a progressive spinal disorder that causes three-dimensional deformation of the vertebrae.

Although it is still not clear exactly why scoliosis occurs, its progression is known to be due, in part, to the force of gravity (i.e., the force of gravity does not cause the disorder, it simply helps it to progress).

Let us try to explain this in simple terms: our spine is like a tower of building bricks that serves to support us, and the bricks distribute evenly the weight it has to bear. If we have scoliosis, some of our bricks are not correctly shaped.
As a result, they are not properly aligned and our tower (spine) may have curve(s) in it. A spine with curve(s) is no longer able to distribute evenly the weight it has to bear; indeed, this presses down harder on the inside of the scoliotic curve, and less on its outside. 

If our spine is well supported, this effect can be lessened, because the support allows the blocks to realign, and this, in turn, reduces the extent of the curve(s). Conversely, without support, the bricks will slide even further to one side, increasing the angle of curvature and shortening the trunk even more.

What does all this mean? That our scoliotic curve will worsen more rapidly unless we continually correct it.

This is why the exercise-based treatment method used at Isico is based on the principle of SELF-CORRECTION: affected youngsters learn to intervene independently to control and align their spine as correctly as possible, thereby countering its tendency to collapse in the direction of the scoliotic curve.

Let us consider another aspect. On a spinal X-ray, we can measure the degrees of curvature present. The angle of curvature is actually the sum of two components: the deformity itself and the effect of postural sagging in the direction of the curve. The contribution of this second component is largely dependent on our capacity for “self-correction”.

How can we distinguish between these two components, i.e., actual bone deformity and postural sagging, so as to be able to intervene effectively on each of them? Again, on an X-ray, but in this case, it must be taken with the patient lying down, so that the degrees of curvature caused by postural sagging disappear, and all that can be seen, and measured, are those due to the deformity itself.

One study, now rather old but still valid, published in Spine in 1976 (Standing and supine Cobb measures in girls with idiopathic scoliosis, G Torell, A Nachemson, K Haderspeck-Grib, A Schultz), showed that postural sagging in scoliosis causes, on average, 9 degrees of curvature (ranging from 0 to a maximum of 20), and that the degrees attributable to postural failure are independent of the severity of the curve. Another interesting study published in Spine, in this case in 1993 (Diurnal variation of Cobb angle measurement in adolescent idiopathic scoliosis, M Beauchamp, H Labelle, G Grimard, C Stanciu, B Poitras, J Dansereau), shows that back “fatigue” can also affect the Cobb angle. In this study, youngsters with moderate to severe scoliosis (an average of 60 Cobb degrees) were X-rayed in the morning and then in the evening. The X-ray taken in the evening showed an average 5-degree increase in curve severity.

What should we do in treatment terms? Clearly, exercises alone cannot alter the actual bone deformity resulting from the scoliosis, which needs to be treated with a combination of exercises and brace wearing.
Nevertheless, specific exercises and self-correction can do a lot to address the problem of postural sagging. And if this “sagging” is responsible for an increased Cobb angle, we need to work hard at our exercises in order to “eat away” at (reduce) the part of the curve that is due to this component.

A perfectly straight back? That’s pretty rare!

It is as rare to have a perfectly straight back and perfectly symmetrical body as it is to have scoliosis, a condition that affects no more than 5% of the population. Scoliosis is linked to different factors that influence the shape and development of the spine in the three planes of space.
What causes it? In most cases, we still don’t know.

On the other hand, we are very familiar with how the condition typically evolves. We know that scoliosis that is left untreated will worsen as an effect of bone growth. Therefore, to limit its effects, it is essential to obtain an early diagnosis and undertake an effective treatment, guided by experts in the field.  

  • When should scoliosis be treated? Let’s look at two key parameters  

There are two elements that tell us the seriousness of a case of scoliosis, namely, the amplitude of the curve (measured in Cobb degrees) and the individual’s bone age (Risser sign).

Briefly, with regard to the amplitude of the curve

  • 0 – 10 Cobb degrees → no scoliosis
  • 10 – 15 Cobb degrees → mild scoliosis
  • 16 – 34 Cobb degrees → moderate scoliosis
  • 35 – 44 Cobb degrees → moderately severe scoliosis
  • 45 Cobb degrees or more → severe scoliosis

Instead, to evaluate bone age we use a scale of 0 to 5 (where 5 corresponds to complete bone maturation).

The phase in a youngster’s development in which scoliosis is most likely to worsen is the pubertal growth spurt, a period in which their growth rate speeds up and they grow considerably. On average, this phase begins between the ages of 11 and 13 years in girls, and 12 and 14 years in boys, and this generally corresponds to the passage from level 0 to level 1 on the Risser scale.

The subsequent phases, of course, are not risk free, but in most cases the speed of growth progressively declines, and for this reason, so does the risk of progression of scoliosis.

  • 0-10 Cobb degrees: is it correct that even if there’s an asymmetry we don’t need to worry?

If a patient has an X-ray that shows a curve measuring less than 10 Cobb, he/she will not be diagnosed with scoliosis and no treatment will be prescribed, only further monitoring of the situation according to how much the patient is still expected to grow.

Nevertheless, the image will show some asymmetry of the spine, and on observing this, even slight, curvature, patients and parents quite often become alarmed.

No one likes to be told that their spine or their child’s spine is “asymmetrical”, and they can be sceptical or even disappointed to learn that nothing needs to be done.

  • “We don’t all come out of the same mould!”

It is probably as rare to have a perfectly straight spine and a perfectly symmetrical trunk as it is to have scoliosis.

We often tell our patients that “we don’t all come out of the same mould”, in order to explain, in simple terms, that everyone of us presents some (more or less visible) physical asymmetries. 

Think of the different parts of the body that we have two of. If we were to measure the precise length and size of our hands, feet, arms and legs, we would almost certainly find they show some minor differences.

In the presence of a difference in length of the lower limbs (typical during growth), for example, it is quite common to find a proportional inclination of the pelvis and, consequently, of the spine.

In this case, however, the scoliosis serves a “functional” purpose, as its contributes to the maintenance of the body’s balance and can thus be interpreted as a useful compensatory response and unlikely to worsen as the youngster grows.

My kid is always slouching: bad posture or a medical problem?

In today’s digital age, the incredible exponential curves of technological growth and innovation are increasingly reflected in curves of another kind, namely those affecting our spines, as we assume various odd and unnatural positions when using our electronic devices.  

Parents are the first to notice their youngsters’ tendency to adopt these awkward and unattractive positions. The most frequent is the hunched back position, where the upper spine, shoulders and head are bent forward in relation to the rest of the body.
Consequently, we now see countless humps like that of Quasimodo, the famous “Hunchback of Notre Dame”.

The tendency to slouch or adopt slumped postures is prevalent among the young. Youngsters (and adults too) often assume incorrect postures simply because it is easier and requires less effort.
As a result, they allow the force of gravity to take its toll on their backs without trying to counteract it. 
Some situations, however, require careful assessment, as incorrect postures can sometimes indicate a spinal disorder.

Initially, it is up to parents to check their children’s backs, and if they have any doubts at all, they should seek the opinion of expert medical spine specialists.

How do you tell the difference between incorrect posture and a spinal disorder?

If you have the youngster stand in front of you with his/her back exposed and look at him/her sideways on, you should immediately notice the classic shape of the back, created by two natural and opposing curves; starting from the base of the spine and moving upwards, you will see the first, lower curve.
Known as lumbar lordosis, this is a physiological curve in which the lumbar spine appears more anteriorly positioned and concave. Immediately above it, you will see that the dorsal spine instead shows a posterior convex curve.

In normal conditions, these two curves are harmonious and not too pronounced. However, if, on observing the youngster, you notice that one curve is more pronounced or protruding or that both are marked, then this could be a sign of a spinal disorder. In such cases, screening by a qualified professional or a consultation with a specialist spine doctor is strongly recommended.

In the same way, you might notice that the youngster’s back appears flat, with the physiological curves barely visible or not visible at all. This profile, too, can indicate the presence of a spinal disorder.

The spinal disorder most commonly associated with the rounded back or hunchback posture is hyperkyphosis, i.e. excessive curvature of the thoracic spine, evident on clinical examination as posterior protrusion of a section of the thoracic spine, often with the protruding vertebrae clearly visible under the skin.  

But how can a parent distinguish between incorrect posture and hyperkyphosis, a fairly frequent condition among youngsters?
Incorrect posture is always easily remedied simply by reminding the youngster to stand up straight: indeed, in this case, this action is enough to straighten his/her back completely.
In the presence of a spinal disorder, on the other hand, he/she will show more or less marked stiffness: even when he/she tries to stand up straight, part of the spine will remain curved due to the disease having stiffened his/her back.

Long kyphosis is another frequent vertebral alteration. In this case, the thoracic convexity extends down as far as the lumbar vertebrae, invading the space normally occupied by the upper part of the lumbar lordotic curve: the back, therefore, presents with a long convexity that reaches down to the base of the back.

Dorsal hyperkyphosis and long kyphosis are sometimes caused by Scheuermann disease, which is characterised by a wedge-shaped deformity of the vertebral bodies with anterior thinning of the vertebrae.
This makes it difficult and sometimes impossible for affected youngsters to hold their back straight: as a result, they become curled up like hedgehogs, and unfortunately, their growth exacerbates the vertebral deformity.

Conclusion

Like scoliosis, spinal deformities in the sagittal plane must be diagnosed early to allow timely and effective treatment. Families have the important task of trying to spot spinal disorders instead of simple cases of poor posture. Whenever they are in any doubt, they should always contact a specialist spine doctor for a proper diagnosis and necessary treatment.